
Match Day Spotlight 2016: Family Medicine, Round 2
Pixie Sanders, a recent fourth-year medical student who matched to Banner University Medical Center South for family medicine, gives us her expert advice on succeeding in medical school and beyond.

Medical Student Editor
University of Toledo College of Medicine and Life Sciences
I'm Sandy Tadros and I'm a 2015 graduate of Washington University of St. Louis with a kind-of strange major in philosophy-neuroscience-psychology. I currently attend The University of Toledo College of Medicine and Life Sciences in the class of 2019. I spent an interesting two years working for the Writing Center at WashU's campus and am exploring a career as a physician-journalist.
In my free time I watch way too much Netflix, and I love cooking.
Pixie Sanders, a recent fourth-year medical student who matched to Banner University Medical Center South for family medicine, gives us her expert advice on succeeding in medical school and beyond.
Friday afternoon psychiatry didactic sessions are a holy time among medical students. A golden weekend rapidly approaches and the afternoon, typically spent trudging through paperwork, is instead spent listening to residents talk with minimal effort required to listen. At the end of a frantic third year of rotating, sometimes it’s nice to just set the busy work down and take it all in. Granted, I’ll actually have to learn the info at some point before the test, but for one afternoon it’s nice to be passive.
After four tough years of medical school and student loans, facing down seven more grueling years of training, aspiring neurosurgeons enter a residency interview process that is as bizarre as it is effective.
Farrah Fong, a recent fourth-year medical student who matched to Rutgers-Robert Wood Johnson University Hospital for family medicine, gives us her expert advice on succeeding in medical school and beyond.
Diane Brackett, a recent fourth-year medical student who matched to Massachusetts General Hospital for pathology, gives us her expert advice on succeeding in medical school and beyond.
Samantha Margulies, a recent fourth-year medical student who matched to Yale-New Haven Hospital for obstetrics and gynecology, gives us her expert advice on succeeding in medical school and beyond.
We stood in the shadows, a staggered line of nurses, students and surgeons in matching blue scrubs and masks. It was the middle of the night. Our tired bodies sagged against the walls, our bloodshot eyes dancing between the clock above and the gasping life below. A young man was dying in the operating room. He lay on the cutting table with his arms splayed wide, like a martyred saint stretched upon the cross.
My recent psychiatry clerkship inspired me to examine racial relations during third-year rotations. This reflection originated from a physician submitting a particularly disturbing evaluation of me. She wrote: “[The student does not] recognize and address personal limitations or behaviors that might affect their effectiveness as a physician … [The student is] defensive, rigid, intense and intrusive; unable to see nuances in human behavior that is necessary for analyses of the human psyche; lower emotional quotient than peers.” Her response left me with an open-jawed, stuporous gaze. I could not believe that she had made this kind of assessment after interacting with me in only two patient encounters for less than half a day!
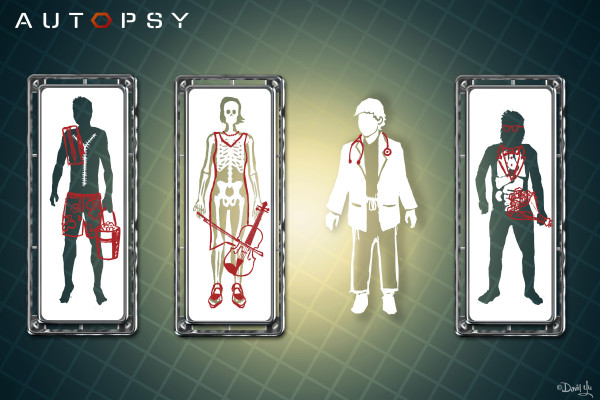
I went through medical school without experiencing the death of a patient I had personally cared for. In contrast to what may be seen on the trauma service, my surgery clerkship was full of routine procedures: appendectomies and cholecystectomies, port placements, excisions of pilonidal cysts, and miscellaneous “ditzels,” as pathologists may refer to them as. Sure, I have had patients who were quite sick and did not have much time left to live. For example, I once performed a neurologic exam on a comatose teenager in the ICU, whose arteriovenous malformation had bled wildly out of control despite prior neurosurgery. But with the constant shuffling of rotations that medical students must endure, I was always in and out of patients’ lives before they had a chance to leave mine.
I recently had the opportunity to shadow a local occupational medicine physician over spring break. I arrived at his office Monday morning expecting a brief day of clinic, maybe some conversation over lunch; maybe I get lucky and he pays for my sandwich. Within minutes of meeting him, though, the physician offered to host me for the entire week on a “mini-rotation.”

Like poker, medicine has certain rules — patterns of clinical symptoms and lab findings each correlating with a specific spectrum of prognoses that vary in likelihood, the differential diagnosis. Physicians are like seasoned card players, trained to maintain composure and incorporate numerous variables into logical, calculated decisions at what seems like a “dealer’s table” of outcomes. Sometimes, we hedge our bets that the patient will self-resolve, so we elect not to treat; other times, we act conservatively with a battery of tests and pre-emptive therapy.
While I could list close to 100 lessons, I believe focusing on three of the most important ones would aid other future health professionals in managing and ultimately treating the chronic illnesses that will become even more prevalent in many of our future patients. As a disclaimer, I do not claim to be an expert on this topic, but these ideas spring from my own personal reflections.

Contributing Writer
Oklahoma School of Community Medicine
Medical student at University of Oklahoma School of Community Medicine in Tulsa, OK.